

Last updated on August 11th, 2026 at 07:10 pm
Medically Reviewed by Dr. Anil D’Cruz, MBBS, MS – General Surgery, DNB – General Surgery, FRCS (Hon.) | Written by Dr. Subhamoy Mukherjee, Advanced Bioinformatics Diploma, PH.D. in Oncology
Mouth cancer can be treated without surgery in early stages (Stage I–II) using radiotherapy, which achieves cure rates of 70–90% when the cancer is caught early. In advanced stages (III–IV), surgery is usually recommended, but it is often combined with non-surgical treatments — chemotherapy, immunotherapy, and targeted therapy — to improve outcomes and reduce recurrence. Whether you need surgery depends entirely on the stage, size, and location of your cancer, and your overall health.
If you or someone you love has just been diagnosed with mouth cancer, the first question is usually:
“Do I have to have surgery?”
That fear is completely understandable. Surgery for mouth cancer — which can involve removing part of the jaw, tongue, or floor of the mouth — changes lives in ways that go far beyond the operating room.
The good news is that many patients, especially those diagnosed early, never need surgery at all. And even for those who do, non-surgical treatments often play a critical role in their recovery plan.
This guide walks you through exactly which non-surgical treatments are available, when each one works best, and what to realistically expect at each stage of mouth cancer.
Not sure which stage your cancer is at or which treatment applies to you?
Our MedicoExperts Tumor Board reviews your case and provides a specific treatment recommendation within 24-48 hours — at no cost. →
What is Mouth Cancer?
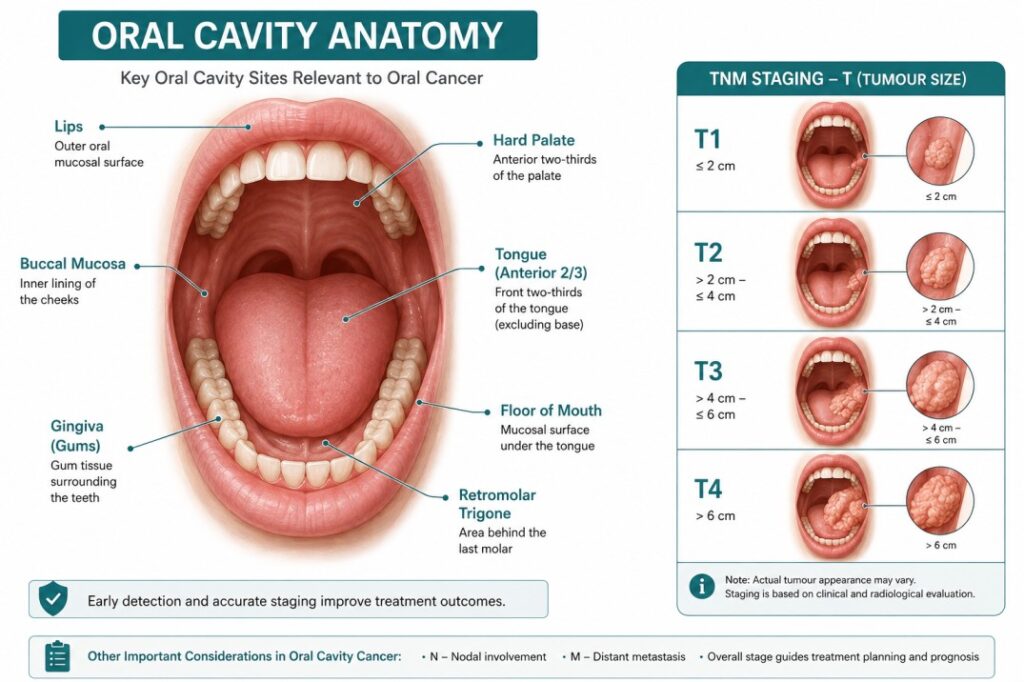
Mouth cancer (medical term: oral cavity carcinoma, ICD-10: C06.9) forms in your oral cavity — the lips, tongue, inner lining of the cheeks, roof of the mouth (hard palate), floor of the mouth, and the gums. It falls under the broader category of head and neck cancers.
The vast majority of mouth cancers — over 90% — are squamous cell carcinomas, meaning they start in the flat, thin cells (squamous cells) that line the inside of the mouth. The remaining cases include adenocarcinoma (from salivary glands) and rarer subtypes.
Doctors describe how far mouth cancer has spread using the TNM staging system:
- T (Tumour) — the size and local extent of the primary tumour (T1 to T4a/T4b)
- N (Nodes) — whether cancer has spread to nearby lymph nodes in the neck
- M (Metastasis) — whether cancer has spread to distant organs (lungs, liver, bones)
Understanding your TNM classification is the single most important factor in determining whether non-surgical treatment alone can work for you.
What are the Symptoms of Mouth Cancer?
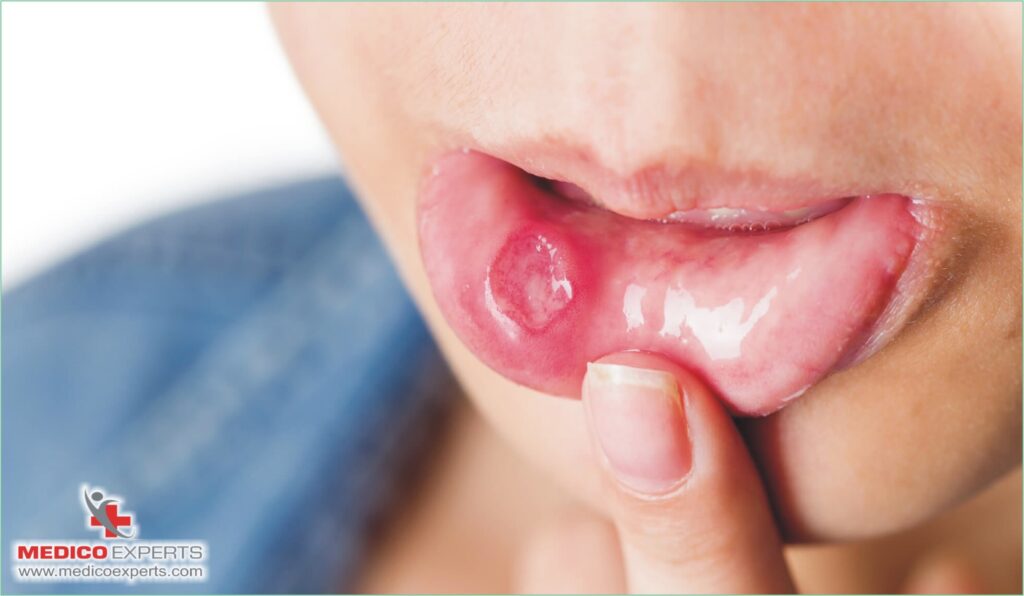
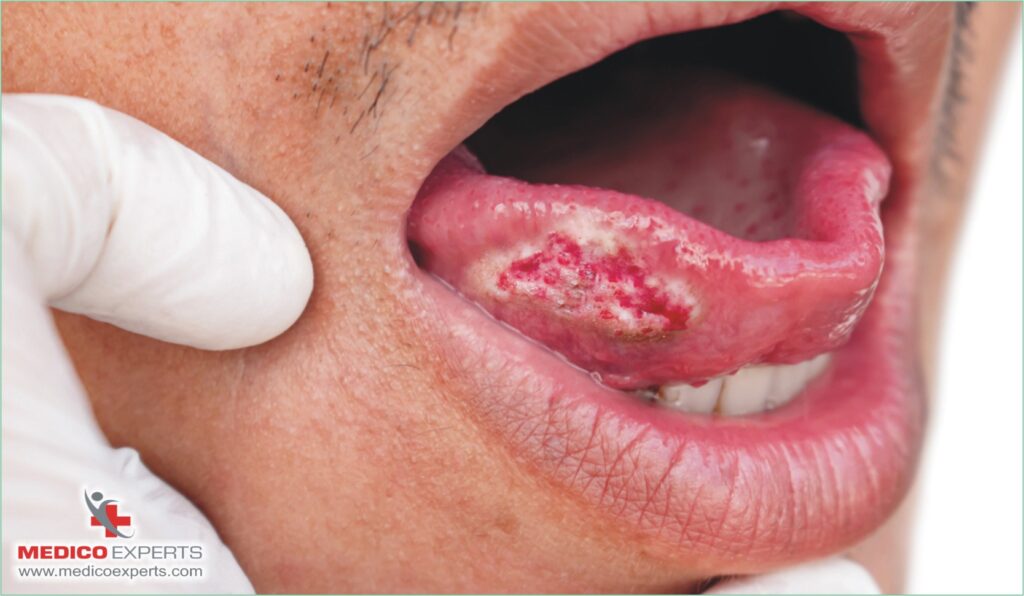
Mouth cancer often gives early warning signs that are easy to dismiss. If any of the following have lasted more than two to three weeks, consult a doctor — early detection is the single biggest factor in whether surgery can be avoided:
- You notice a white or red patch on your gums, tongue, or the inner lining of your cheek that does not heal on its own.
- A sore or ulcer in your mouth or on your lip has been present for more than three weeks without healing.
- You feel a lump or thickening in your cheek, on your tongue, or on the floor of your mouth.
- You have unexplained pain or numbness anywhere in your mouth, tongue, lips, or throat.
- Your speech has changed — words feel harder to form, or your voice sounds different.
- You find it increasingly difficult to swallow, chew, or open your mouth fully.
- A lump has appeared in your neck that has been there for more than two to three weeks.
- You have lost weight without trying to diet.
Important: These symptoms do not confirm cancer — many have benign causes. But because mouth cancer responds dramatically better to treatment when caught early, any symptom lasting more than 2–3 weeks deserves a medical evaluation. Do not wait.
When Can Mouth Cancer Be Treated Without Surgery? — Stage-by-Stage Guide
The most important factor in deciding whether you need surgery is the stage of your cancer at diagnosis. Per NCCN 2024 guidelines, surgery is the preferred treatment at all stages where it is feasible — but radiation therapy (and proton therapy) are accepted alternatives for patients who decline surgery, or where surgery is medically inappropriate. Here is what the evidence shows:
| Stage | Surgery? | Non-Surgical Alternative | 5-Year Survival |
| Stage I (T1, N0, M0) | Preferred (tumour resection) | RT alone or Proton Therapy alone — curative in most cases | 70–90% |
| Stage II (T2–T3, N0, M0) | Preferred | RT ± concurrent chemotherapy; Proton Therapy for organ-sparing | 50–70% |
| Stage III (any T, N1, M0) | Preferred + adjuvant CRT | Chemoradiotherapy (CRT) if surgery declined/contraindicated | 40–60% |
| Stage IV (extensive spread / M1) | Preferred where resectable; unresectable = non-surgical | Immunotherapy + targeted therapy + chemo; palliative RT / proton RT for symptom control | 15–40% |
Sources: NCCN Clinical Practice Guidelines, Head & Neck Cancers v1.2024 – October 9, 2023; American Cancer Society (ACS, 2024); AJCC 8th Edition Cancer Staging Manual.
The honest picture: Stage I and early Stage II mouth cancers give you the strongest chance of avoiding surgery entirely. The later the stage, the more likely surgery becomes part of a combined plan — but even then, non-surgical treatments before or after surgery dramatically improve survival outcomes. For patients where surgical side-effects (speech, swallowing, facial appearance) are a concern, the non-surgical route deserves full discussion with a multidisciplinary team.
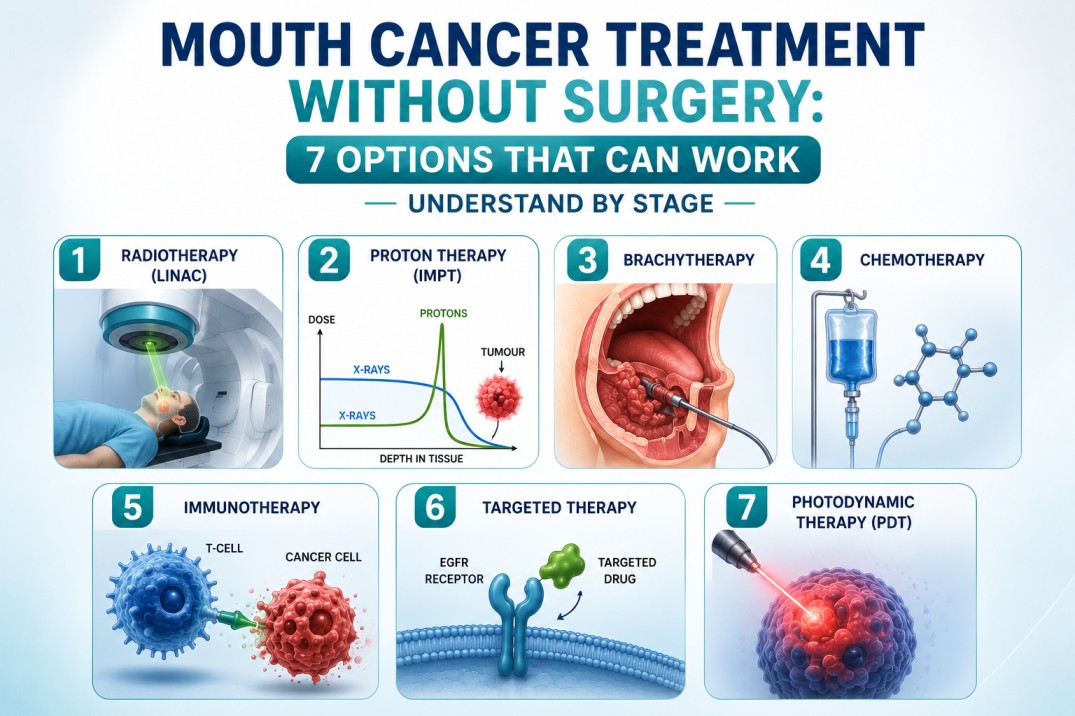
7 Non-Surgical Treatment Options for Mouth Cancer
Quick Comparison Table: (Best referenced alongside the detailed sections below)
| Treatment | Best used when | Can it cure? | With surgery? | Key side effect |
|---|---|---|---|---|
|
1
Radiotherapy
External beam / IMRT
|
Stage I–II primary cure Stage III–IV post-surgery prevention |
✓ Yes — Stage I–II | ✓ Yes — adjuvant | Dry mouth, mucositis |
|
2
Proton Beam Therapy
IMPT — advanced radiation
Evidence updated 2025
|
Stage I–IV where organ-sparing is critical — jaw bone, brainstem, salivary glands; re-irradiation of recurrent tumours |
✓ Yes — equivalent to IMRT with less toxicity 90.9% 5-yr survival (Lancet Phase III, 2025) |
✓ Yes — adjuvant or definitive | Less dry mouth than IMRT; specialist proton centre required |
|
3
Brachytherapy
Internal radiotherapy
|
Small surface tumours Stage I Tongue / floor of mouth |
✓ Yes — early stage | ~ Sometimes | Mouth swelling, discomfort |
|
4
Chemotherapy
Cisplatin / carboplatin
|
Stage III–IV with radiation; induction or adjuvant alongside surgery | ✗ Rarely alone | ✓ Yes — neoadjuvant / adjuvant | Nausea, fatigue, low immunity |
|
5
Immunotherapy
Pembrolizumab / Nivolumab
|
Unresectable / recurrent / metastatic; PD-L1 CPS ≥ 1; after platinum chemo progression | ~ Partial; some complete responses | ~ Sometimes | Immune reactions (skin, colon, lungs) |
|
6
Targeted Therapy
Cetuximab — EGFR blocker
|
EGFR-positive tumours Stage III–IV; cisplatin-intolerant patients; recurrent / metastatic HNSCC | ✗ Rarely alone | ✓ Yes — with radiotherapy | Skin rash, infusion reactions |
|
7
Photodynamic Therapy
PDT — light-activated
|
Very early surface lesions Stage 0–I; precancerous patches; palliation in advanced cases | ✓ Yes — very early stage only | ~ Sometimes | Photosensitivity, local swelling |
← Swipe left / right to see all columns
Note: This table is a quick reference only. Suitability depends on your TNM stage, tumour location, overall health, and oncologist assessment. Proton therapy evidence updated August 2026 — TORPEdO Phase III trial, The Lancet, December 2025. Sources: NCCN Head & Neck Cancer Guidelines v1.2024; American Cancer Society 2024.
Not sure which treatment applies to your case? Our MedicoExperts Tumour Board — including proton therapy and radiation oncology specialists — reviews your reports and gives a written recommendation within 48 hours.
WhatsApp us to get a free tumour board review →1. Radiotherapy (External Beam Radiation / IMRT) — The Primary Non-Surgical Cure Option
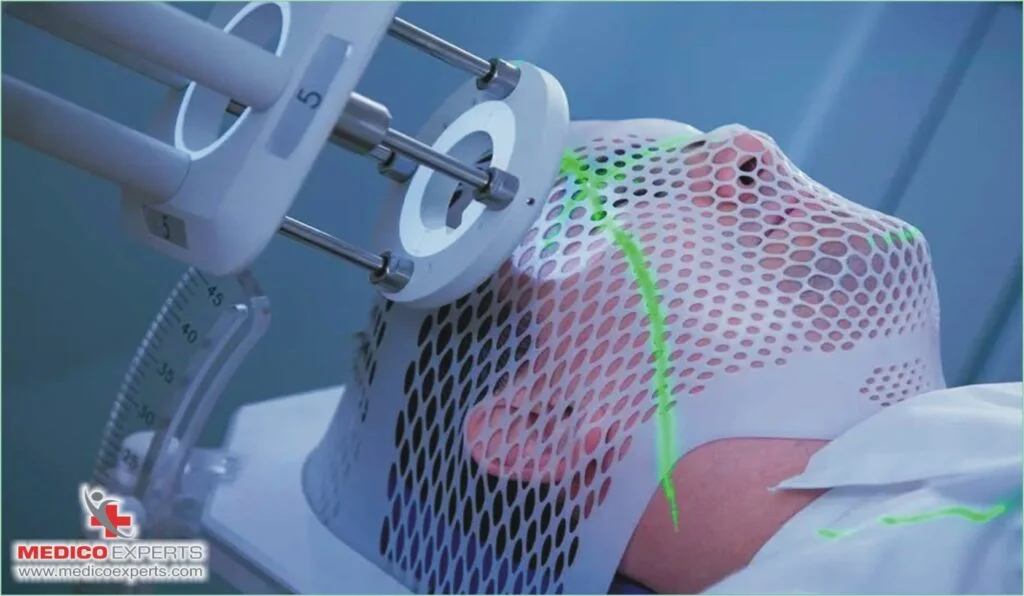
Radiotherapy uses precisely targeted beams of high-energy radiation to destroy cancer cells by damaging their DNA. For early-stage mouth cancer, external beam radiotherapy — specifically Intensity-Modulated Radiation Therapy (IMRT) — is the most commonly chosen non-surgical treatment and carries genuine curative intent: the goal is to eliminate the cancer entirely, not just control it.
How it works: You receive treatment five days a week for approximately 5–7 weeks (25–35 sessions), each lasting about 15–30 minutes. IMRT uses computer-controlled beams of varying intensities that precisely conform to the tumour shape, reducing dose to surrounding healthy tissues.
When it works as a standalone cure: Stage I and many Stage II mouth cancers respond excellently to radiotherapy alone. A 2022 review in Oral Oncology found that definitive radiotherapy for T1–T2 oral tongue cancers achieved 5-year local control rates of 78–88%.
CyberKnife — Robotic Radiosurgery: CyberKnife is a robotic photon-beam radiosurgery system that targets tumours with sub-millimetre accuracy using conventional X-ray radiation delivered by a robotic arm. It is particularly useful for recurrent or complex tumours requiring extreme precision. Important: CyberKnife uses photon (X-ray) beams, not proton beams — it is a different technology from Proton Therapy. Both are forms of advanced radiotherapy, each with different indications (see Treatment #2 for Proton Therapy).
Side effects to expect: Dry mouth (xerostomia) is the most common long-term effect. Soreness in the mouth (mucositis), difficulty swallowing during treatment, and skin changes at the treatment site are expected and manageable. Most improve after treatment ends.
→ Click to Learn more about CyberKnife treatment
2. Proton Beam Therapy (IMPT) — Advanced Radiation With Less Damage to Healthy Tissue
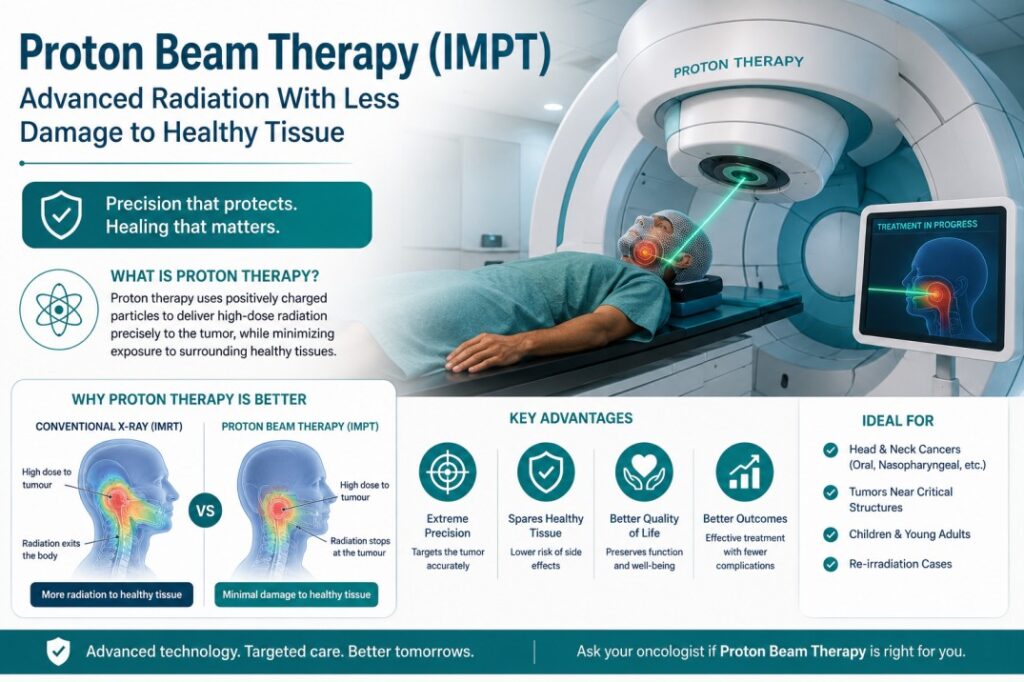
Proton Beam Therapy (PBT) uses beams of protons — positively charged particles — instead of the X-rays used in conventional radiotherapy. This physical difference produces a fundamentally different dose distribution inside the body, one that makes proton therapy particularly valuable for mouth and head-and-neck cancers where critical structures (salivary glands, jaw, spinal cord, brainstem) lie very close to the tumour.
Why protons behave differently from X-rays: When protons enter the body, they travel to a precise depth and then deposit the bulk of their energy in a sharp peak called the Bragg Peak — after which the dose drops to nearly zero. X-rays and photon beams, by contrast, continue through the body beyond the tumour, delivering radiation to healthy tissue on the exit path. For mouth cancer, this means proton therapy can treat the tumour while delivering significantly lower doses to the jaw bone (reducing risk of osteoradionecrosis), salivary glands (reducing dry mouth), swallowing muscles (reducing dysphagia), and the oral cavity itself.
The key clinical evidence:
- Phase III TORPEdO Trial (The Lancet, December 2025): 440 patients at 21 centres randomised to proton therapy (IMPT) or conventional IMRT. At 5 years: 90.9% of proton patients alive vs 81% with IMRT — a 10% absolute improvement in overall survival. Proton patients had less feeding-tube dependence, less dry mouth, better swallowing outcomes, and less immune suppression.
- 2024 Prospective Oral Cavity Trial (ScienceDirect, September 2024): In oral cavity cancer specifically, proton therapy demonstrated lower doses to all critical organs at risk vs photon plans, including significantly better results for oral cavity mean dose, mandible, constrictors, and larynx — directly challenging the previous assumption that oral cavity cancers benefit less from proton therapy.
- NCCN 2024 Head & Neck Guidelines: Proton Beam Therapy (PBT) explicitly listed as a treatment option, specifically noted as useful “near the skull base, brain stem, optical nerve, or spinal cord; or to preserve parotid function.” IMRT remains the preferred standard; PBT is the recommended upgrade for cases with critical structure proximity.
When proton therapy is most appropriate for mouth cancer:
- Tumours close to critical structures such as the jaw bone, brainstem, spinal cord, or major salivary glands
- Young patients where long-term radiation toxicity (dry mouth, jaw complications) is a major quality-of-life concern
- Patients who cannot tolerate the side effects of conventional radiotherapy
- Re-irradiation: when a patient needs radiation for a recurrent tumour in an area that has already been irradiated
- Adjuvant (post-surgery) treatment where precise dose control is needed to spare reconstructed tissues
Proton Therapy vs Conventional Radiotherapy (IMRT) — The Key Differences:
| Factor | Conventional IMRT | Proton Beam Therapy (IMPT) |
| Radiation type | X-rays (photons) | Protons (charged particles) |
| Exit dose | Yes — photons continue through the body beyond the tumour | No — dose stops at the Bragg Peak depth |
| Dry mouth risk | Higher (more dose to salivary glands) | Lower — significantly better salivary gland sparing |
| Jaw bone risk | Higher dose to mandible | Lower — reduces osteoradionecrosis risk |
| Swallowing impact | Higher dose to constrictor muscles | Lower — better long-term swallowing outcomes |
| 5-year survival (Phase III) | 81% (TORPEdO trial, 2025) | 90.9% (TORPEdO trial, 2025) |
| Availability | Widely available at most cancer centres | Specialist proton centres required (limited in India currently) |
| Cost | Standard radiation therapy cost | Higher — specialist equipment required |
Availability in India: Proton therapy centres in India are currently limited but expanding. Apollo Proton Cancer Centre (Chennai) is the first and largest proton therapy centre in South Asia and is NCCN-affiliated. Tata Memorial Hospital (Mumbai) and AIIMS Delhi have ongoing expansions. For international patients considering India for proton therapy, MedicoExperts can coordinate access to the appropriate specialist centres.
Side effects: Proton therapy produces fewer side effects than conventional radiotherapy, particularly for dry mouth, swallowing difficulties, and jaw complications. Fatigue, local skin reaction at the entry site, and mucositis within the radiation field can still occur but are typically milder and shorter-lasting than with IMRT.
→ Click here to Learn more about Proton Therapy
3. Brachytherapy (Internal Radiotherapy) — Targeted Radiation From Inside
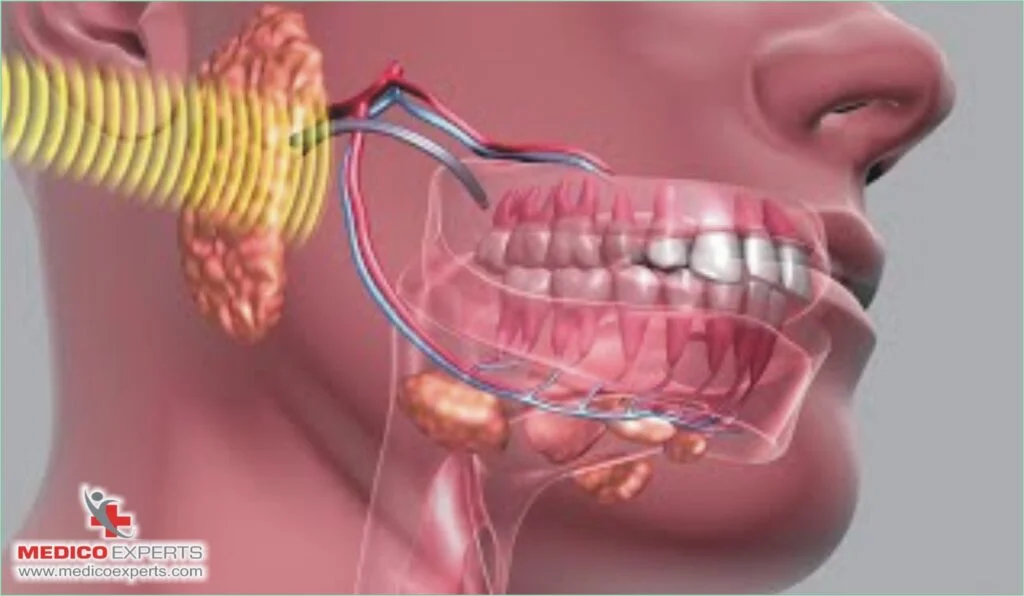
Brachytherapy places small radioactive implants directly inside or adjacent to the tumour, delivering an extremely high and focused radiation dose to the cancer while sparing surrounding tissues. It is particularly effective for small, well-defined mouth cancers — especially on the tongue, floor of the mouth, and lip.
How it works: Under general anaesthesia, thin radioactive needles or tubes are inserted directly into the tumour site. The implants remain in place for 1 to 8 days. The cancer cells receive a concentrated dose that would be impossible to deliver safely with external radiation.
When it is recommended: Stage I oral cancers that are small (under 4cm), accessible, and have not spread to lymph nodes. It may also follow external radiotherapy as a “boost” dose to the primary tumour site.
Side effects: Swelling and discomfort in the mouth are expected during and immediately after the implants are in place. Most patients recover within 2–4 weeks. Dry mouth and taste changes are possible long-term effects.
4. Chemotherapy — Systemic Cancer-Cell Destruction
Chemotherapy uses powerful medicines (most commonly cisplatin or carboplatin for mouth cancer) that travel through the bloodstream to destroy rapidly dividing cancer cells throughout the body. For mouth cancer, chemotherapy is almost never used as a standalone treatment — instead, it plays a supporting role alongside radiotherapy or surgery.
When it is used:
- Concurrent chemoradiotherapy (CRT): Chemotherapy given alongside radiation makes cancer cells more sensitive to radiation, improving outcomes for Stage III–IV mouth cancer. Cisplatin is the preferred concurrent agent per NCCN 2024.
- Adjuvant chemotherapy: Given after surgery to reduce the risk of recurrence when pathological risk factors (positive margins, extranodal spread) are present.
- Induction (neoadjuvant) chemotherapy: Given before surgery or radiotherapy to shrink a large tumour, making it more treatable. TPF regimen (docetaxel, cisplatin, 5-FU) is NCCN-preferred for induction.
- Palliative chemotherapy: For Stage IV cancers that cannot be cured, chemotherapy extends survival and manages symptoms.
Side effects: Nausea, fatigue, reduced immunity, mouth sores, hair loss, and temporary kidney stress with cisplatin-based regimens. Side effects are carefully managed and largely temporary.
5. Immunotherapy — Training Your Own Immune System to Fight Cancer
Immunotherapy uses medications called checkpoint inhibitors to remove the signals that cancer cells use to hide from your immune system. For mouth cancer, two NCCN-approved checkpoint inhibitor drugs are available, with a third used in combination in certain advanced cases.
When it is used:
- First-line treatment for recurrent or metastatic head and neck squamous cell carcinoma with PD-L1 CPS ≥1 — a checkpoint inhibitor alone or combined with platinum-based chemotherapy and 5-FU (KEYNOTE-048 trial, The Lancet, 2019)
- Second-line treatment after platinum-based chemotherapy has stopped working — a different checkpoint inhibitor has shown proven survival benefit in this setting (CheckMate 141 trial)
- Unresectable Stage IV mouth cancer where surgery is not possible
PD-L1 testing is essential: Before immunotherapy, your oncologist should test your tumour’s PD-L1 Combined Positive Score (CPS). A CPS ≥1 qualifies for checkpoint inhibitor monotherapy; higher CPS scores correlate with better response. If this test has not been done, ask your doctor to request it — the result can completely change which treatment pathway is recommended.
Side effects: Unlike chemotherapy, immunotherapy side effects are immune-related rather than affecting all fast-dividing cells. The most common reactions involve the skin (rash), colon (diarrhoea), lungs (pneumonitis), and liver. These are manageable when caught early and are typically far less debilitating than traditional chemotherapy side effects for most patients.
→ Learn more about Immunotherapy
6. Targeted Therapy — Precision Treatment for Specific Cancer Signals
Targeted therapy uses drugs designed to attack specific proteins or pathways that cancer cells depend on for growth. For mouth cancer, the most important target is EGFR (Epidermal Growth Factor Receptor), which is overexpressed in approximately 80–90% of head and neck squamous cell carcinomas.
The key approved drug in this category is an EGFR-blocking monoclonal antibody — a precision medicine that latches onto the EGFR protein on cancer cells and blocks the growth signals they rely on. It is approved for:
- Locally advanced head and neck cancer combined with radiotherapy — particularly as an alternative for patients who cannot tolerate standard platinum-based chemotherapy
- Recurrent or metastatic mouth cancer in combination with platinum-based chemotherapy
Evidence: The landmark Bonner trial (NEJM, 2006) found that this EGFR-blocking antibody combined with radiotherapy improved median overall survival from 29.3 months to 49 months compared to radiotherapy alone in locoregionally advanced head and neck cancer — nearly 20 additional months of survival.
Side effects: The most distinctive side effect is an acne-like skin rash, which paradoxically correlates with better treatment response — patients who develop the rash tend to respond better to the drug. Infusion reactions can occur during treatment but are manageable with pre-medication given before each dose.
→ Click here to Learn more about Targeted Therapy
7. Photodynamic Therapy (PDT) — Light-Activated Treatment for Surface Cancers
Photodynamic therapy (PDT) uses a light-sensitive medication (photosensitising agent) and a specific wavelength of laser light to destroy cancer cells. It is one of the least invasive non-surgical options, but has a very specific and narrow application window.
How it works: You receive a photosensitising drug (most commonly ALA) that is absorbed preferentially by cancer cells. Laser light is then directed at the tumour, causing the drug to generate reactive oxygen that destroys cancer cells from the inside.
When it is appropriate:
- Very early (Stage 0 or Stage I) surface cancers of the lip, tongue, or buccal mucosa
- Precancerous lesions (oral leukoplakia, erythroplakia) at high risk of becoming cancerous
- Palliation in advanced cases where conventional treatment options are exhausted
Limitation: PDT is not suitable for cancers that have grown deeper than a few millimetres into tissue or have spread to lymph nodes. It is a precision tool for the earliest-stage disease only.
Side effects: Temporary photosensitivity — avoid bright sunlight and strong indoor lighting for several days after treatment. Local swelling and discomfort resolve within 2–4 weeks.
→ Click here to Learn more about Photodynamic therapy
Can Tongue Cancer Be Treated Without Surgery?
Tongue cancer is one of the most common types of mouth cancer, and the question of surgery is especially charged — because tongue surgery can significantly affect speech and swallowing. The reassuring answer is that for many tongue cancer patients, non-surgical treatment — including both conventional radiotherapy and proton beam therapy — is genuinely effective.
Anterior tongue (front two-thirds): Small tumours (T1–T2) that are accessible and have not spread to lymph nodes are often treated with brachytherapy alone, with excellent local control rates. External radiotherapy (IMRT) is an alternative. Where salivary gland or jaw bone preservation is a concern, proton beam therapy is increasingly preferred.
Base of tongue (posterior third, oropharynx): Base of tongue cancers, particularly those caused by HPV, respond exceptionally well to chemoradiotherapy. HPV-positive base of tongue cancers have significantly better outcomes with radiation-based treatment. Proton therapy is especially valuable here because it reduces dose to the swallowing structures (constrictors) and the contralateral salivary glands — reducing long-term swallowing difficulties and dry mouth that can persist for years.
Larger tongue cancers (T3–T4): For tumours that have grown deep into the tongue muscle or spread to multiple lymph nodes, surgery (partial glossectomy) followed by adjuvant radiotherapy is typically the recommended approach. Proton therapy as adjuvant treatment post-surgery is an emerging option to reduce post-operative radiation toxicity.
What to Do if Chemotherapy Is Not Working — Your Next Options
If standard chemotherapy has not produced the results your doctor hoped for, that does not mean you have run out of options. Here is what to explore:
Step 1: Request a Tumour Board Review
A multidisciplinary tumour board — oncologists, radiation specialists, surgeons, and pathologists — reviews your complete case together and agrees on a revised treatment recommendation. MedicoExperts operates a virtual tumour board that reviews cases remotely, delivering a written recommendation within 48 hours.
Step 2: Test for Immunotherapy Eligibility
Ask your oncologist to test your tumour’s PD-L1 Combined Positive Score (CPS). This is a biomarker test that determines whether your cancer is likely to respond to checkpoint inhibitor immunotherapy. Patients with a CPS of 1 or above qualify for this treatment; those with a score of 20 or above tend to have the strongest responses. If this test has not been done, request it — the result can completely change the recommended treatment pathway.
Step 3: EGFR Testing for Targeted Therapy
Approximately 80–90% of mouth cancers overexpress a protein called EGFR (Epidermal Growth Factor Receptor), which cancer cells use to fuel their growth. If an EGFR-blocking targeted therapy has not been tried, it may be an option — either alone or combined with radiotherapy, especially for patients who cannot tolerate platinum-based chemotherapy regimens.
Step 4: Consider Proton Therapy Re-Irradiation
For patients who have already received conventional radiotherapy and have a recurrence in the same area, re-irradiation with proton beam therapy is an emerging option. Proton therapy’s superior dose control allows radiation to be delivered to a previously irradiated tumour site with significantly less damage to surrounding tissues that have already received their lifetime radiation dose. This is a specialist indication — discuss with a proton therapy centre.
Step 5: Explore Clinical Trials
India has a growing number of active oncology clinical trials investigating next-generation immunotherapy combinations, antibody-drug conjugates, and novel targeted agents. Tata Memorial Hospital Mumbai, AIIMS, Apollo Proton Cancer Centre (Chennai), and other major centres can advise on open trials.
Step 6: Palliative Care Is Not Giving Up
If curative intent is no longer the medical goal, high-quality palliative care manages pain, maintains nutrition, improves quality of life, and in many cases extends survival significantly. This is a specialised medical discipline — not “end of treatment” — and should be integrated from the time of advanced cancer diagnosis.
Mouth Cancer Treatment Without Surgery in India — What MedicoExperts Offers
India is home to some of the world’s most advanced cancer treatment infrastructure, with world-class radiation oncology equipment — including proton therapy centres — experienced multidisciplinary teams, and treatment costs that are 40–70% lower than the UK, US, or Australia for equivalent-quality care.
Proton Therapy in India: Apollo Proton Cancer Centre (Chennai) is South Asia’s first and largest proton therapy centre and is an NCCN-affiliated institution. For mouth cancer patients where proton therapy is appropriate, MedicoExperts can coordinate assessment and referral to the right centre.
MedicoExperts connects patients — both from India and internationally — to specialist oncology teams for non-surgical mouth cancer treatment through:
- Virtual Tumour Board Reviews: Send your reports, biopsy slides, and imaging online. A multidisciplinary panel of oncologists — including radiation oncology specialists — reviews your case and delivers a written treatment recommendation within 48 hours.
- Proton Therapy Assessment: For patients who may benefit from proton therapy, we coordinate specialist assessment at proton-capable centres and provide a comparison with conventional radiation therapy options.
- Specialist Second Opinions: If you have received a treatment plan and want to verify whether proton therapy or another non-surgical option applies to your case.
- Treatment Coordination: Hospital admission, oncologist appointments, accommodation, visa assistance, and post-treatment follow-up for Indian and international patients.
- International Patient Support: NRI families and international patients receive dedicated case managers coordinating between home country and India-based treating teams.
Surgery vs Non-Surgical Treatment for Mouth Cancer — Honest Comparison
Both surgical and non-surgical approaches are medically legitimate — the right choice depends entirely on your individual case. Here is an honest comparison:
| Factor | Surgery | Non-Surgical Treatment (RT / Proton / Chemo / Immuno) |
| NCCN preference | Preferred for early and locally advanced resectable cancers | Alternative (standard-equivalent for Stage I–II); primary for unresectable |
| Treatment duration | Procedure: hours; recovery: weeks to months | IMRT/Proton: 5–7 weeks daily; chemo: cycles; immuno: infusions |
| Cure potential (Stage I–II) | Very high | Very high (equivalent for Stage I–II per clinical evidence) |
| Speech impact | Possible — depends on extent and reconstruction | Minimal (dry mouth, mucositis during treatment — typically resolves) |
| Swallowing impact | Possible — depends on extent | Possible mucositis during RT; proton therapy reduces long-term dysphagia |
| Dry mouth (long-term) | Not directly caused by surgery | IMRT: common; Proton Therapy: significantly less |
| Recurrence risk | Low with clear surgical margins | Low with adequate dose and field coverage |
| Best for advanced disease | Stage III–IV resectable (with adjuvant CRT/proton RT) | Stage III–IV unresectable; as combined with surgery at all stages |
The key message: Neither approach is universally “better.” For early-stage cancers, radiotherapy (including proton therapy) and surgery deliver equivalent cure rates in most locations. For advanced cancers, the two are most effective together. Your oncologist’s recommendation should be based on your specific staging, tumour location, overall health, and your own quality-of-life priorities.
When to See a Doctor
See a doctor or dentist urgently — within one week — if any of the following apply:
- A mouth ulcer, sore, or patch has not healed after three weeks
- You have found a lump in your neck, mouth, or on your tongue in the last few weeks
- You are experiencing progressive difficulty swallowing or opening your mouth
- You have been diagnosed with mouth cancer and have not yet received a treatment plan from a specialist oncologist
- Your current treatment is not working and you have not had a multidisciplinary tumour board review
- You want to know whether proton therapy may reduce side effects compared to conventional radiotherapy for your specific case
- You are experiencing severe pain, bleeding, or unexplained weight loss alongside oral symptoms
For Indian patients: If you do not have access to a specialist oncologist locally, a virtual tumour board review through MedicoExperts allows you to receive specialist input — including assessment for proton therapy eligibility — without travelling. Contact us for a 24-48-hour turnaround consultation.
Key Takeaways

Mouth cancer does not always require surgery — and understanding your stage and treatment options is the most important step:
- Early-stage mouth cancer (Stage I–II) can often be cured with radiotherapy alone — with survival rates equivalent to surgery for many tumour sites.
- Proton Beam Therapy (IMPT) is now an important addition to the non-surgical treatment landscape, offering equivalent tumour control to conventional radiotherapy with significantly better preservation of the jaw, salivary glands, and swallowing function. A 2025 Phase III trial showed a 10% improvement in 5-year survival over conventional IMRT.
- Seven non-surgical treatments are now available: radiotherapy (IMRT), proton beam therapy, brachytherapy, chemotherapy, immunotherapy, targeted therapy, and photodynamic therapy. Most work best in combination.
- Tongue cancer responds well to non-surgical treatment, especially HPV-positive base of tongue cancers — and proton therapy is particularly valuable for reducing long-term swallowing and dry-mouth problems.
- If chemotherapy has not worked, you still have options: PD-L1 testing for immunotherapy, EGFR testing for cetuximab, proton therapy re-irradiation for recurrence, and clinical trials.
- The most important step is a multidisciplinary tumour board review before committing to any treatment plan.
If you have been diagnosed with mouth cancer and are wondering whether surgery can be avoided — or want to know whether proton therapy, immunotherapy, or another non-surgical approach applies to your case — MedicoExperts’ Tumour Board can help.
Frequently Asked Questions (FAQs):
Q1. How long does mouth cancer treatment without surgery take?
A standard course of external beam radiotherapy (IMRT) or proton beam therapy for mouth cancer typically takes 5–7 weeks, with daily sessions five days a week. Each session lasts 15–30 minutes. If chemotherapy is given alongside radiation (concurrent chemoradiotherapy), cisplatin is usually administered weekly or in 3-weekly cycles during the radiation course. After completing treatment, imaging scans are performed at 8–12 weeks to assess the cancer’s response. Total active treatment time is approximately 6–8 weeks.
Q2. What is the last stage of mouth cancer?
A: Stage 4 is the last stage of mouth cancer. At this stage, the cancer has spread to nearby tissues and organs like the oral cavity and jaw. It can be of any size.
Q3. Is mouth cancer curable at stage 3?
A: The mouth cancer will be limited to the mouth or one lymph node and in most cases easier to treat and cure in stages 0 to 3. Cancer has spread to nearby tissues and other organs if it is in stage 4 and it needs an aggressive treatment plan.
Q4. Where are oral cancers most commonly found, and does location affect treatment options?
A: Oral cancers most commonly arise on the tongue (lateral border and base), the floor of the mouth, the lips, and the buccal mucosa. Location significantly affects treatment options: tongue and floor-of-mouth cancers are often candidates for brachytherapy or definitive radiotherapy in early stages. For tumours near the jaw bone, skull base, or major salivary glands, proton beam therapy is increasingly preferred to reduce damage to these critical structures. An oncologist assesses location as one of several factors in designing your non-surgical or combined treatment plan.
Q5. Can mouth cancer be treated without surgery?
Yes — mouth cancer can be treated without surgery, particularly in early stages. Stage I and many Stage II mouth cancers are routinely treated with radiotherapy or proton beam therapy alone, achieving 5-year survival rates of 70–90%. In more advanced stages, non-surgical treatments like chemotherapy, immunotherapy, and targeted therapy are used alongside or instead of surgery depending on the patient’s specific situation. Per NCCN 2024 guidelines, the decision always depends on the stage, size, and location of the cancer, confirmed by a specialist multidisciplinary team.
Q6. How to cure mouth cancer permanently?
Surgery is the only way to remove the mouth cancer. The doctors may also need to remove some of the lymph glands during the process. In some cases, the area around the cancer also needs to be removed to stop the cancer from coming back.
Q7. Can tongue cancer be treated without surgery?
Tongue cancer can be treated with surgery or non-surgical options like radiotherapy, and chemotherapy. Doctors use one of these treatment options or combinations of them. The treatment approach will completely depend on the size of the cancer and how far it has spread.
1. Siegel RL, et al. Cancer statistics 2024. CA Cancer J Clin. 2024;74(1):12-49. DOI: 10.3322/caac.21820
2. Bonner JA, et al. Radiotherapy plus cetuximab for squamous-cell carcinoma of the head and neck. N Engl J Med. 2006;354(6):567-578. DOI: 10.1056/NEJMoa053422
3. Burtness B, et al. Pembrolizumab alone or with chemotherapy versus cetuximab with chemotherapy for recurrent or metastatic squamous cell carcinoma of the head and neck (KEYNOTE-048). Lancet. 2019;394(10212):1915-1928. DOI: 10.1016/S0140-6736(19)32591-7
4. National Cancer Institute. Head and Neck Cancers — Patient Version. NCI. 2024. https://www.cancer.gov/types/head-and-neck
5. American Cancer Society. Oral Cavity and Oropharyngeal Cancer Survival Rates. ACS. 2024. https://www.cancer.org/cancer/types/oral-cavity-and-oropharyngeal-cancer/detection-diagnosis-staging/survival-rates.html
6. NHS UK. Mouth Cancer — Treatment. NHS. 2023. https://www.nhs.uk/conditions/mouth-cancer/treatment/
7. NCCN Clinical Practice Guidelines in Oncology: Head and Neck Cancers. Version 1.2024. National Comprehensive Cancer Network. October 2023. https://www.nccn.org
8. Gupta B, et al. Oral cancer in India continues in epidemic proportions: evidence base and policy initiatives. Int Dent J. 2013;63(1):12-25. DOI: 10.1111/idj.12007
9. Mayo Clinic. Mouth Cancer — Symptoms and Causes. Mayo Clinic. 2024. https://www.mayoclinic.org/diseases-conditions/mouth-cancer/symptoms-causes/syc-20350997
10. PubMed. Photodynamic therapy for oral cancer. PMID: 8804893. https://pubmed.ncbi.nlm.nih.gov/8804893/
11. TORPEdO Trial: Proton vs IMRT for Head and Neck Cancer. The Lancet. December 2025. Phase III randomised trial, 440 patients, 21 centres. 90.9% vs 81% five-year overall survival (proton vs IMRT). DOI: 10.1016/S0140-6736(26)00314-4
12. Proton Therapy vs Photon Plans for Oral Cavity Cancer. ScienceDirect / International Journal of Radiation Oncology. September 2024. Prospective trial showing significantly lower OAR doses with proton therapy in oral cavity cancer patients. DOI: 10.1016/j.ijrobp.2024.025203
13. Liu X, Zhang Z. Advances in radiotherapy for mouth neoplasms: emerging technologies and future perspectives. Discover Oncology. Springer Nature. July 2025. Review of IMRT, proton therapy, and FLASH for oral cancers. DOI: 10.1007/s12672-025-03249-w
14. https://www.mayoclinic.org/diseases-conditions/mouth-cancer/symptoms-causes/syc-20350997
15. https://pubmed.ncbi.nlm.nih.gov/8804893/
16. https://www.cancer.gov/about-cancer/treatment/types/chemotherapy
17. https://www.cancer.org/cancer/types/oral-cavity-and-oropharyngeal-cancer/treating/radiation-therapy.html
18. https://www.nhs.uk/conditions/mouth-cancer/treatment/
19. https://www.mayoclinic.org/diseases-conditions/mouth-cancer/symptoms-causes/syc-20350997
This article is for informational and educational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always seek the advice of your qualified oncologist or healthcare provider regarding your specific cancer diagnosis, staging, and treatment options. Treatment decisions for mouth cancer must be made in consultation with a qualified medical team.
Relevant Articles For You
Oral cancer is one of the most common cancer types that is becoming a growing problem in many parts of the world. With new cases exceeding 640,000 annually. However, with the advancement of technology, experience, and…..Read More
Recommendations To Understand Different Treatments
Do you know, that you can increase the lifespan of cancer patients by targeted therapy while significantly reducing the side…..Read More
Are you anxious because you or your dear one is diagnosed with cancer? More so, when you are not sure about the success of the…..Read More
Does surgery for removing the brain tumor itself bring shivers in you? Lots of stress and anxiety with fear of the unknown start rushing in…..Read More
Medically Reviewed by MedicoExperts Editorial & Clinical Review Board


